This study aimed to compare the survival rates and periodontal health outcomes of two types of mandibular fixed retainers—3-strand round twisted (RT) and 8-strand rectangular braided (RB)—each bonded to all six anterior teeth. A total of 133 orthodontic patients (median age: 24.6 years; interquartile range: 17.2–32.4 years; range: 15.1–49.8 years) were randomly assigned in a 1:1 ratio to receive either an RT or RB fixed retainer. Inclusion criteria included the presence of all permanent mandibular incisors and canines, absence of caries, restorations, fractures, or periodontal disease. Individuals with inadequate oral hygiene prior to debonding were excluded. The primary endpoint was the occurrence of the first retainer failure, while secondary measures included periodontal index, bleeding on probing, plaque index, gingival index, and probing depth. Randomization was achieved using permuted blocks of 4, 6, or 8 with allocation concealment via sealed, opaque envelopes. Due to the nature of the intervention, blinding was not feasible. Follow-up evaluations were conducted at baseline, 3, 6, 12, 18, and 24 months post-placement. Retainer survival was analyzed through Cox regression, while periodontal outcomes were evaluated using generalized estimating equations to assess the effects of treatment, time, tooth, and treatment-time interaction. Baseline characteristics were comparable across groups; one participant withdrew from the trial. Over the 2-year period, retainer failure occurred in 37 of 66 (56.1%) patients in the RT group and 32 of 66 (48.5%) in the RB group (log-rank test, P = 0.55). The adjusted hazard ratio for failure was 0.69 (95% CI: 0.42–1.12; P = 0.13), with neither age nor gender influencing the results. All periodontal measures remained similar between groups and stable across time points. Both retainer types demonstrated high failure rates (overall 52.3%), with no significant difference in survival or periodontal health between the RT and RB designs.
Introduction
Regardless of the type or severity of malocclusion or the applied treatment approach, dental arch changes are anticipated over time, and the degree of posttreatment relapse remains unpredictable, as no reliable predictors have been identified [1]. A recent systematic review indicated that changes in mandibular anterior alignment following orthodontic treatment are minimal and show no relationship with pretreatment irregularity, clinical environment, retainer type, or adjunctive interventions [2]. These minimal alterations may, however, reflect consistent adherence to retention protocols within the analyzed studies.
Several randomized clinical trials (RCTs) have investigated the success [3, 4], cost-effectiveness [5], patient adherence [6], and acceptance [7] of various retention strategies. Comparisons of different retention methods—such as vacuum-formed retainers, enamel stripping, positioners, and canine-only bonded retainers [3, 4, 8, 9]—though showing some variability, generally reveal no significant differences in maintaining dental alignment [9]. Fixed retainers (FRs) bonded to all six mandibular anterior teeth tend to provide superior stability compared to canine-only FRs [10] and represent a practical choice when even minimal incisor movement is undesirable. Nevertheless, these retainers, while effective at preserving mandibular anterior alignment, exhibit higher failure rates than vacuum-formed alternatives [11].
Mandibular FRs bonded to all six anterior teeth vary in cross-sectional geometry, strand number, alloy type, and wire structure (twisted vs. braided), and are commonly used in orthodontic practice [12–14]. Following Dahl and Zachrisson’s recommendations [15], many clinicians continue to use round multistranded wires for retainer fabrication. However, evidence from the Netherlands suggests that a substantial number of orthodontists prefer square or rectangular wires [13], possibly due to earlier reports of dental arch changes associated with round wire retainers [16, 17]. More recently, Kocher et al. examined the long-term outcomes of a 0.016 × 0.022-inch braided stainless-steel retainer bonded to all six mandibular anterior teeth, finding it effective for maintaining alignment [18, 19]. Yet, these studies were retrospective and did not include a direct comparison between rectangular and round twisted (RT) retainers.
To date, no randomized controlled trial has rigorously evaluated the clinical performance of rectangular wire FRs. Therefore, the present study compared a 0.0215-inch 3-strand RT retainer with a 0.0265 × 0.0106-inch 8-strand rectangular braided (RB) retainer regarding survival rate and periodontal health over a 24-month period. The null hypothesis posited that there would be no significant differences between the two retainer types.
Materials and Methods
The study received ethical approval from the Warsaw Medical Chamber (approval no. KB/956/14; October 23, 2014). Written consent was obtained from every participant, and for minors, from their legal guardians. The clinical trial was not registered.
Study design, participants, and setting
This investigation followed a two-arm, parallel-group randomized controlled design conducted in a single private orthodontic practice (P.S.F). Participant enrollment took place between December 2014 and April 2018. Eligible individuals were between 15 and 50 years old at the time of appliance removal and had a complete set of permanent mandibular canines and incisors. Additional inclusion criteria required the absence of active dental caries, restorations, fractures, or any signs of periodontal disease, with the retention plan limited to a fixed retainer spanning from canine to canine. Exclusion criteria included inadequate oral hygiene, active periodontal inflammation, need for surgical or restorative procedures, or the use of removable retainers in combination with fixed ones. Two months before the scheduled debonding, potential participants were informed about the trial’s purpose, design, and procedures and invited to participate. Individuals requesting time to decide were given several days before confirming their participation, after which those who consented proceeded with the treatment protocol outlined in the Interventions section.
Sample size calculation
The required sample size was determined to detect a 25% difference in first-time failure rates between groups (expected 50% vs. 25%) with a significance level of 0.05 and power of 80% (β = 0.8). The estimate was derived from prior findings by Pandis et al. [20], who observed nearly 50% failure within two years after retainer placement. Based on these assumptions, each study arm required at least 58 participants.
Randomization process
Random allocation was carried out using an online random number generator available at www.sealedenvelope.com. Random permuted blocks of 4, 6, or 8 patients ensured balanced assignment between the two groups. Concealment of allocation was achieved by using pre-prepared, sequentially numbered, opaque envelopes. The practice manager, acting as the study coordinator, was responsible for opening each envelope in order and recording the group assignment.
Interventions
Approximately one month before appliance removal, an alginate impression of each participant’s mandibular arch was obtained and sent to the laboratory within 24 hours, accompanied by a specification indicating the assigned retainer type: a 0.0215-inch stainless steel 3-strand round twisted (RT) wire (Ortho Organizers, Lindenberg, Germany) or a 0.0265 × 0.0106-inch 8-strand rectangular braided (RB) Bond-a-Braid wire (Reliance Orthodontic Products, Itasca, Illinois, USA). Around two weeks before debonding, all patients received professional cleaning and scaling performed by an experienced hygienist.
The bonding protocol followed standardized clinical steps: insertion of cheek retractors, cleaning and drying of the lingual surfaces of the six anterior teeth, etching with 37% phosphoric acid, rinsing, and re-drying. The retainer was stabilized in place with three pieces of dental floss, followed by the application of adhesive primer (Transbond XT; 3M Unitek, Monrovia, California) and a layer of light-cured composite resin (Transbond Supreme LV; 3M Unitek). Polymerization was completed by light curing, and particular care was taken to avoid saliva contamination during the bonding process. All retainers were placed by the same orthodontic assistant, who had over 15 years of clinical experience performing this procedure.
Outcomes
This investigation evaluated two main categories of outcomes: the primary outcome, defined as the first recorded instance of retainer failure (retainer survival), and secondary outcomes, which encompassed periodontal health parameters including the periodontal disease index (PDI) according to Russel [21], bleeding on probing (BOP), plaque index (PI) following Loe and Silness [22], gingival index (GI), and pocket depth (PD). Measures of dental arch stability and patient satisfaction will be presented in a subsequent publication.
Data collection
Measurements were conducted at six intervals: baseline (immediately after debonding and retainer placement), and subsequently at 3, 6, 12, 18, and 24 months post-placement. All evaluations were carried out by the same examiner (E.W.), an orthodontist with over ten years of clinical experience. Participants were instructed to contact the clinic promptly in the event of any retainer failure. Each visit concluded with scheduling of the next follow-up appointment to ensure continuity of data collection.
At every assessment, retainers were first examined visually for defects such as adhesive discoloration or material loss, followed by manual testing to confirm adequate bonding between the wire and the six anterior teeth. If any failure was identified, its type (debonding, wire fracture, or complete detachment) and specific tooth location were recorded. In cases of debonding, the adhesive remnant index was applied to classify the extent of remaining adhesive into four levels: absence of bond on the tooth surface, less than 50% coverage, greater than 50% coverage, and full coverage of 100%.
After inspection of retainer integrity, periodontal parameters were measured. The PDI was calculated as the mean of individual scores across the six mandibular anterior teeth, ranging from 0 (healthy periodontium) to 8 (advanced destruction). BOP represented the percentage of sites showing bleeding within 10 seconds of probing at six locations per tooth. The PI reflected the average plaque accumulation score across these teeth, rated from 0 (no plaque) to 3 (abundant plaque). GI values ranged from 0 (no inflammation) to 3 (severe inflammation), while PD was measured with a periodontal probe at the lingual surfaces of all six teeth. The same examiner (E.W.) performed both retainer and periodontal assessments to maintain consistency.
Blinding
Masking was not feasible in this trial because the retainer designs—3-strand round twisted (RT) and 8-strand rectangular braided (RB)—were visually and structurally distinct, making concealment during examinations impossible.
Statistical analysis
Descriptive statistics were computed at baseline for each intervention group and across all follow-up intervals (3, 6, 12, 18, and 24 months). Retainer survival was analyzed using a Cox proportional hazards model adjusted for age and sex, and the proportional hazards assumption was verified using Schoenfeld residuals.
For periodontal variables, population-averaged generalized estimating equation (GEE) models were employed. Given the non-normal distributions and low frequency of some outcome levels, certain measures were dichotomized based on clinical relevance: GI (0 vs. >0), PD (≤1 mm vs. >1 mm), and PDI (0 vs. >0). Binary outcomes were analyzed using logistic regression models including treatment, time, tooth, and treatment × time interaction as predictors, with empirical standard errors and an independent correlation structure. The PI, treated as a continuous variable, was analyzed using a Gaussian GEE model with empirical standard errors and an exchangeable correlation matrix. BOP, based on event counts, was modeled using a Poisson GEE framework with empirical standard errors and an independent correlation structure.
Missing data were handled using a multiple imputation approach with chained equations (fully conditional specification) [23], employing 20 burn-in iterations and 40 imputations. Depending on the variable, logit, Gaussian, or Poisson models were used. The GEE models were re-run on the imputed dataset to verify robustness. All analyses were performed using Stata (version 16.1; StataCorp, College Station, TX), SAS (version 9.4; SAS Institute, Cary, NC), and R (version 3.6.1; R Foundation for Statistical Computing, Vienna, Austria).
Results
Participants
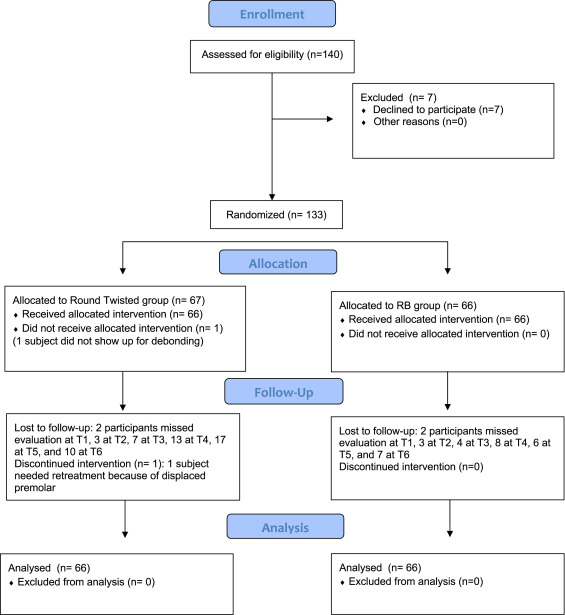
A total of 133 patients (42 males and 91 females) with a median age of 24.6 years (25th percentile: 17.2; 75th percentile: 32.4; range: 15.1–49.8 years) were randomly assigned to one of two groups: the 3-strand round twisted (RT) wire group (n = 65; 22 males, 43 females) or the 8-strand rectangular braided (RB) wire group (n = 66; 19 males, 47 females), both bonded across the six mandibular anterior teeth. Participant progression through the study is illustrated in Figure 1 (CONSORT diagram). Of the 133 enrolled, 132 completed the intervention as assigned; one participant withdrew after requesting additional orthodontic treatment for a displaced premolar and was excluded from analysis. Four participants missed one to three follow-up appointments but were retained in the statistical analyses.
|
|
|
Figure 1. CONSORT flow diagram illustrating participant progression throughout the study |
Baseline data
At the start of the trial, the two treatment groups demonstrated similar demographic and clinical profiles. Periodontal measurements recorded at baseline (during debonding) confirmed that participants in both groups exhibited overall healthy periodontal conditions (Table 1).
Table 1. Baseline characteristics of the groups
|
Characteristics |
RT |
RB |
|
Age |
23.9 (17.0-31.6) |
27.2 (17.5-33.2) |
|
Sex, % males |
34.3% |
28.8% |
|
PDI |
0 (0-1) |
0 (0-1) |
|
BOP |
0.2 (0.1-0.3) |
0.2 (0.1-0.3) |
|
PI |
0.3 (0.1-0.5) |
0.3 (0.2-0.5) |
|
GI |
0 (0-0.5) |
0 (0-0.5) |
|
PD |
1.5 (1-2) |
1.5 (1-2) |
Note. Values are median (25th percentile-75th percentile).
Survival analysis
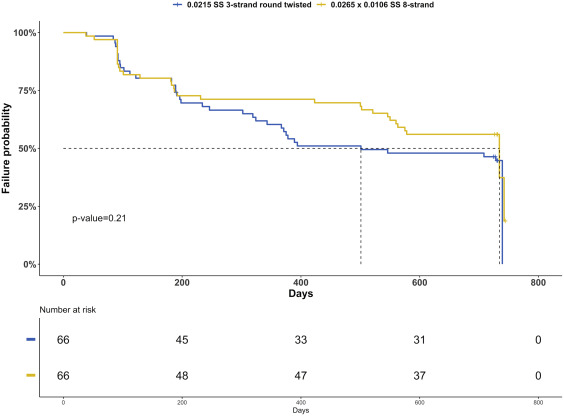
During the two-year follow-up, 37 of the 66 participants (56.1%) in the RT group and 32 of the 66 participants (48.5%) in the RB group experienced at least one instance of retainer failure. The ratio of failed teeth to the total number of teeth among subjects with initial failures was 25.2% for the RT group and 21.9 percent for the RB group (Table 2), suggesting that multiple-site failures occurred in some individuals. Additionally, two participants in the RT group lost their retainers entirely, whereas none in the RB group did. However, the majority of failures were localized to a single tooth—most frequently the central or lateral incisors—while failures involving canines were uncommon (Supplementary Table I).
The proportional hazards assumption was met, and Kaplan-Meier survival curves depicting patient retention over time for both retainer types are shown in Figure 2. No significant difference in failure rates was identified between the two groups (log-rank test, P = 0.55). The calculated hazard ratio (HR) was 0.69 (95 percent CI: 0.42–1.12; P = 0.13). Furthermore, neither age (HR: 1.01; 95 percent CI: 0.98–1.04; P = 0.52) nor gender (HR: 0.67; 95 percent CI: 0.39–1.15; P = 0.15) showed any significant association with the likelihood of retainer failure (Table 3).
Table 2. Summary of retainer failure types across study groups
|
Variable |
RT group |
RB group |
P value* |
|
Total number of teeth in patients who experienced their first failure |
222 |
192 |
— |
|
Number of teeth showing failures (%) |
56 (25.2%) |
42 (21.9%) |
— |
|
Adhesive Remnant Index |
0.17 |
||
|
Debonding with no adhesive left on the tooth surface |
13 |
12 |
— |
|
Debonding with less than 50% of adhesive remaining |
13 |
5 |
— |
|
Debonding with more than 50% of adhesive remaining |
13 |
20 |
— |
|
Debonding with complete (100%) adhesive left on tooth surface |
2 |
2 |
— |
|
Wire breakage |
0 |
1 |
— |
|
Complete loss of retainer |
12 |
0 |
— |
|
Indeterminate cause of failure |
3 |
2 |
0.03 |
∗Determined by Fisher exact test.
|
|
|
Figure 2. Kaplan-Meier survival plots by type of retainer |
Table 3. HRs from Cox regression for the type of retainer using imputed data for unobserved failures from losses to follow-up and censoring for unobserved failures
|
Variables |
HR (95% CI) |
P value |
|
Retainer type |
||
|
RT |
Referent |
|
|
RB |
0.69 (0.42-1.12) |
0.13 |
|
Gender |
||
|
Female |
Referent |
|
|
Male |
0.69 (0.39-1.15) |
0.15 |
|
Age, y, per unit |
1.01 (0.98-1.04) |
0.64 |
Periodontal health
As presented in Supplementary Table 2, approximately 10% of the periodontal index data were missing, which was assumed to have occurred at random.
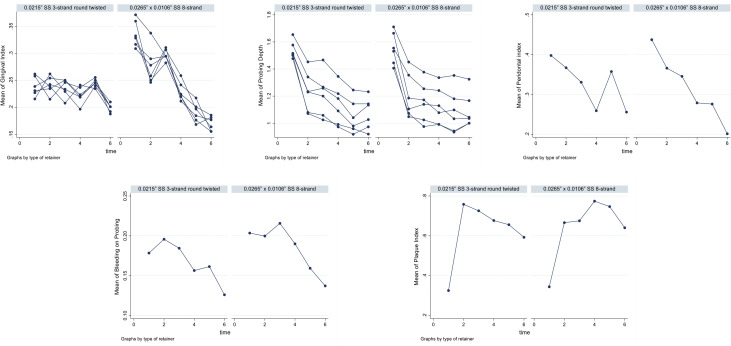
Throughout the two-year follow-up period, all recorded periodontal indicators reflected generally healthy periodontal conditions (Figure 3; Table 4). At the time of debonding, mean scores for the Periodontal Disease Index (PDI), Bleeding on Probing (BOP), Plaque Index (PI), and Gingival Index (GI) were all below 0.5, signifying very good periodontal status at baseline. Over the course of the study, both PDI and BOP showed a minor downward trend, whereas PI exhibited a gradual increase. The GI remained relatively stable in the RT group but displayed a reduction in the RB group. Probing depth (PD) reached its highest value at baseline and then declined as the study progressed (Table 4).
According to the statistical analysis results (Table 5), no significant treatment-by-time interactions were detected for any of the periodontal measures, suggesting that both retainer types followed a similar pattern of change over time. Additionally, there was no significant relationship between retainer type and any periodontal parameter, while time showed a significant effect on all indexes. Tooth type did not influence the GI but was identified as a significant predictor of PD. The findings remained consistent after applying multiple imputations to account for missing data.
|
|
|
Figure 3. Evolution of periodontal indexes per tooth (only for GI and PD) and treatment over time |
Table 4. Periodontal parameters in both groups during follow-up
|
Variable |
T1 |
T2 |
T3 |
T4 |
T5 |
T6 |
||||||
|
RT |
RB |
RT |
RB |
RT |
RB |
RT |
RB |
RT |
RB |
RT |
RB |
|
|
PDI |
0 (0-1) |
0 (0-1) |
0 (0-1) |
0.17 (0-1) |
0 (0-1) |
0 (0-0.67) |
0.11 (0.06-0.22) |
0 (0-0.67) |
0 (0-1) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.17) |
|
BOP |
0.2 (0.1-0.3) |
0.2 (0.1-0.3) |
0.17 (0.1-0.31) |
0.17 (0.8-0.33) |
0.17 (0.08-0.3) |
0.17 (0.08-0.28) |
0.11 (0.06-0.22) |
0.13 (0.06-0.28) |
0.14 (0.04-0.24) |
0.11 (0.06-0.19) |
0.08 (0.04-0.17) |
0.11 (0.03-0.19) |
|
PI |
0.3 (0.1-0.5) |
0.3 (0.2-0.5) |
0.67 (0.38-1.04) |
0.63 (0.33-0.96) |
0.73 (0.38-1) |
0.52 (0.3-0.92) |
0.61 (0.4-1) |
0.54 (0.42-1) |
0.58 (0.33-1) |
0.65 (0.38-1) |
0.58 (0.33-0.83) |
0.58 (0.25-0.83) |
|
GI |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.5) |
0 (0-0.3) |
0 (0-0) |
|
PD |
1.5 (1-2) |
1.5 (1-2) |
1 (1-1.5) |
1 (1-1.5) |
1 (1-1.5) |
1 (1-1.5) |
1 (1-1.5) |
1 (1-1.5) |
1 (1-1.5) |
1 (1-1.5) |
1 (1-1) |
1 (1-1.5) |
Note. Values are median (25th percentile-75th percentile).
T1, baseline, at debonding and retainer placement; T2, 3 mo after retainer placement; T3, 6 mo after retainer placement; T4, 12 mo after retainer placement; T5, 18 mo after retainer placement; T6, 24 mo after retainer placement.
Table 5. Effects of retainer type (treatment), time, and tooth on periodontal parameters
|
Index |
Treatment∗ |
Time |
Tooth |
P value |
|
P values for complete case analysis/after multiple imputation |
Treatment × time |
|||
|
PDI |
0.78/0.74 |
0.003/<0.01 |
Not applicable |
0.89 |
|
BOP |
0.40/0.33 |
<0.001/0.001 |
Not applicable |
0.66 |
|
PI |
1/0.56 |
<0.001/<0.001 |
Not applicable |
0.44 |
|
GI |
0.85/0.86 |
0.01/0.01 |
0.37/0.74 |
0.90 |
|
PD |
0.78/0.85 |
<0.001/<0.001 |
<0.001/<0.001 |
0.44 |
∗Treatment refers to retainer type (RT vs RB).
Discussion
In this trial, we assessed the survival and periodontal condition associated with two types of retainers bonded to all six anterior mandibular teeth (canine to canine). The study hypothesized that no differences would be observed between the groups for any of the outcomes. Over the 2-year follow-up, first-time failures were common (~50%) regardless of the retainer type, with most failures resulting from retainer detachments, while breakages and complete retainer losses were infrequent. Analysis of the adhesive remnant index revealed a similar detachment pattern in both groups: roughly one third of detachments showed no adhesive remaining on the tooth surface, whereas in approximately two thirds, some adhesive remnants were present. Absence of adhesive on the tooth surface suggests weakening at the adhesive–enamel interface, potentially due to moisture contamination during bonding, whereas remnant presence indicates other contributing factors, such as mechanical stress, inadequate polymerization, or poor bond quality. The precise causes of failures could not be determined in this study. A systematic review by Iliadi et al. [24] reported bond failures in mandibular retainers bonded to all six anterior teeth in up to 57% of patients. Several subsequent RCTs have confirmed the relatively high prevalence of retainer failures. The rigorous design of RCTs, with preplanned evaluation time points, likely allows for a more accurate estimation of first-time retainer failure compared with retrospective studies. Therefore, our survival outcomes are consistent with most RCTs reporting on mandibular retainers bonded to six anterior teeth.
A recent systematic review [10] indicated lower failure rates when retainers are bonded only to the canines, suggesting that limiting bonding to canines could reduce failure risk. In our study, failures at the mandibular canines were rare; however, restricting bonding to canines may compromise the stability of mandibular anterior alignment [10,19]. Fixed retainers in the mandible are typically maintained for extended periods, sometimes lifelong [14], which may increase the risk of undesired effects such as decalcification, caries, or gingival and periodontal inflammation due to plaque retention and difficulty in cleaning [1]. In our study, the presence of retainers bonded to six anterior teeth did not appear to negatively affect periodontal health, aligning with a recent systematic review that concluded orthodontic fixed retainers are generally compatible with periodontal health and not associated with severe adverse effects on the periodontium [25]. It is important to note, however, that study participants likely maintained above-average oral hygiene during both treatment and retention, and the follow-up period was relatively short; individuals with poor hygiene were excluded. Similar inclusion and exclusion criteria were used in most RCTs reviewed by Arn et al. [25], where good oral hygiene was an inclusion criterion in five trials, one trial did not specify, two were unclear, and three could not be assessed. Consequently, the conclusion that bonded retention is compatible with periodontal health may primarily apply to patients capable of maintaining good hygiene during the retention phase. In patients unable to sustain ideal oral hygiene, fixed retainers could contribute to periodontal deterioration, as observed by Torkan et al. [26]. Given that lifelong ideal hygiene cannot be guaranteed for all patients, regular follow-ups are essential for those with bonded lingual retainers.
There is evidence indicating that patients with mandibular fixed retainers (FRs) may experience unwanted tooth movements even in the absence of bond failures or wire breakage [16]. These side effects have been linked to unexpected torque changes among adjacent mandibular incisors or to opposing inclinations of contralateral mandibular canines [17,27]. Although the exact mechanism remains unclear, it has been proposed that the retainer may become active, shifting the teeth into undesired positions. This risk appears to be associated with retainers constructed from multiple single stainless-steel filaments twisted into a round wire, as mechanical deformation during biting can cause the wire to untwist, leading to complications. The growing use of rectangular, nontwisted wires for mandibular retainers [14,16] aims to prevent such issues. Supporting this approach, a recent study [18] found that patients who had worn a bonded retainer (RB) in the mandible for over 10 years did not experience complications related to active retainers. In this trial, the choice of wires was informed by previous reports of active retainers; however, unwanted tooth movements were not assessed because they generally manifest after two years of retention [27]. We plan to recall participants five years post-debonding to document any such movements.
Limitations
A key limitation of this trial is the potential for bias due to the lack of blinding during outcome assessment. This study did not evaluate dental arch stability or patient satisfaction with the retention protocol, which will be addressed in a subsequent report. Additionally, the study protocol was not registered prior to commencement; nevertheless, all preselected outcomes were reported, and these outcomes are standard in similar trials, suggesting that selective reporting is unlikely.
Generalizability
The study was conducted in a medium-sized private practice with experienced operators, and all retainers were bonded by a single skilled orthodontic assistant. Consequently, failure rates may differ if less experienced personnel perform the bonding. Periodontal assessments were conducted by one orthodontist rather than a periodontist, so results might vary if assessed by a specialist, although the indexes applied were straightforward and feasible for a nonperiodontist. Since patients in this practice bear all treatment costs and often undergo complex procedures, these findings are generalizable to comparable private practice settings but may not reflect outcomes in other contexts, such as university clinics with postgraduate operators.
Conclusions
The study’s hypothesis—that there would be no difference in first-time failure risk within two years following bonding of retainers to the six anterior mandibular teeth—was not rejected; however, the overall risk of first-time failure was high. In healthy patients maintaining good oral hygiene, mandibular fixed retainers do not appear to adversely affect periodontal tissues in the short term.
Acknowledgments: None
Conflict of interest: None
Financial support: None
Ethics statement: None